Diagnostic and Operative Hysteroscopy: A Practical Review for Surgeons and Gynaecologists
Senior General Surgeon and Minimally Invasive Surgeon, Manish Nursing Home (Dr. Bhandari Piles Hospital), Chittorgarh, Rajasthan, India
Honorary Consultant Surgeon, M.P. Birla Hospital and Research Centre, Chittorgarh, Rajasthan, India
Correspondence: opbhandari@hotmail.com · 8764001124 / 01472-241544 / 9461521485
Abstract
Hysteroscopy is a minimally invasive endoscopic procedure that allows direct visualisation of the uterine cavity, endocervical canal, and tubal ostia, and is considered the gold standard for diagnosis and treatment of intrauterine pathology. This review presents a structured, practice-oriented overview of diagnostic and operative hysteroscopy intended for medical students, postgraduate residents, gynaecologists, and general surgeons seeking to learn the procedure. The review covers relevant anatomy, instrumentation and distension media, diagnostic and operative indications, absolute and relative contraindications, pre-operative assessment and cervical priming, step-by-step operative technique, and the two most clinically significant operative procedures — trans-cervical resection of the endometrium (TCRE) for menorrhagia and trans-cervical resection of sub-endometrial fibroids (TCR-F) using the FIGO classification to guide surgical strategy. Intra-operative and post-operative complications are discussed, with particular attention to fluid overload and dilutional hyponatraemia (the TURP-like syndrome), a preventable but potentially serious complication of monopolar resection. The review concludes with learning objectives stratified by level of training and is accompanied by an operative video supplement demonstrating TCRE and hysteroscopic assessment in infertility and IUD-related presentations, intended to support hands-on learning for surgeons and gynaecologists at every stage of training.
Keywords: hysteroscopy; diagnostic hysteroscopy; operative hysteroscopy; trans-cervical resection of endometrium; TCRE; trans-cervical resection of fibroid; TCR-F; endometrial ablation; Asherman’s syndrome; uterine septum; abnormal uterine bleeding
1. Introduction
Hysteroscopy is a minimally invasive endoscopic procedure that allows direct visualisation of the uterine cavity, endocervical canal, and tubal ostia using a hysteroscope — a thin, lighted telescope inserted through the cervix. It is considered the gold standard for the diagnosis and treatment of intrauterine pathology.
Hysteroscopy can be classified into two broad categories: diagnostic hysteroscopy, used to visualise and assess the uterine cavity, and operative or therapeutic hysteroscopy, used to perform surgical interventions within the uterine cavity itself. The procedure has transformed the management of abnormal uterine bleeding, infertility, and a range of intrauterine structural abnormalities by permitting direct, magnified inspection of the cavity that was previously only inferable from imaging or blind instrumentation.
This review presents a structured, practice-oriented overview of diagnostic and operative hysteroscopy intended for medical students, postgraduate residents, gynaecologists, and general surgeons who wish to learn the procedure, supported by an operative video supplement demonstrating key applications in clinical practice.
2. Relevant Anatomy
A thorough understanding of the relevant anatomy is essential for safe and effective hysteroscopy. The uterine cavity is triangular, lined by endometrium, and measures approximately 6–7 cm in length. The endocervical canal is 2.5–3 cm long and connects the external os to the internal os. The cornual regions, at the junctions of the cavity with the fallopian tubes, are sites of the tubal ostia and are particularly vulnerable to perforation during instrumentation. The myometrium, the muscular wall of the uterus, is approximately 1.5–2.5 cm thick and provides the working margin within which operative resection must remain to avoid perforation.
3. Equipment and Instrumentation
3.1 The Hysteroscope
The hysteroscope is composed of a telescope, available in 0°, 12°, and 30° viewing angles; an outer sheath through which distension media and instruments pass; a working channel that allows passage of operative instruments; and a light source channel that connects to an external cold light source.
3.2 Types of Hysteroscopes
| Type | Outer Diameter | Application |
|---|---|---|
| Diagnostic hysteroscope | 2.7–4 mm | Office / outpatient diagnosis |
| Operative hysteroscope | 5–7 mm | Minor operative procedures |
| Resectoscope | 8–10 mm | TCRE, myomectomy, polypectomy |
| Versapoint system | 5 mm | Bipolar operative hysteroscopy |
| Morcellator hysteroscope | 6.25 mm | Rapid tissue morcellation |
3.3 Distension Media
Normal saline (isotonic) is used with bipolar energy systems and carries no risk of dilutional hyponatraemia. Glycine 1.5%, and sorbitol or mannitol, are hypotonic media used with monopolar systems such as TCRE and rollerball ablation, and require strict fluid monitoring. CO2 gas is used for diagnostic procedures in office settings but carries a small risk of gas embolism.
4. Indications of Hysteroscopy
4.1 Diagnostic Indications
Hysteroscopy is indicated for the evaluation of abnormal uterine bleeding, including menorrhagia, intermenstrual bleeding, and postcoital bleeding; postmenopausal bleeding, to exclude endometrial carcinoma; suspected intrauterine pathology identified on ultrasound or hysterosalpingography; endometrial polyps, submucous fibroids, and intrauterine adhesions consistent with Asherman’s syndrome; infertility work-up, to evaluate the uterine cavity prior to assisted reproductive technology; recurrent pregnancy loss, for structural evaluation of the cavity; congenital uterine anomalies such as septate or bicornuate uterus; assessment of endometrial sampling sites prior to biopsy; retained products of conception, for localisation and removal; lost or embedded intrauterine device localisation and retrieval; cervical stenosis assessment; and follow-up after operative hysteroscopy.
4.2 Operative / Therapeutic Indications
Hysteroscopy permits definitive surgical management of endometrial pathology through trans-cervical resection of the endometrium (TCRE) or endometrial ablation, endometrial polypectomy, and directed endometrial biopsy. Fibroid-related pathology is managed through trans-cervical resection of sub-endometrial or submucous fibroids (TCR-F), staged according to the FIGO classification described in Section 8, and through hysteroscopic myomectomy for infertility-associated submucous fibroids. Intrauterine adhesions are managed by lysis of adhesions for Asherman’s syndrome, using scissors, laser, or electrosurgery. Uterine septa are managed by hysteroscopic metroplasty, dividing partial or complete septa. Other operative indications include removal of an intrauterine device or foreign body, removal of retained products of conception, achieving haemostasis for uterine bleeding, resection of early endometrial cancer in non-surgical candidates, and hysteroscopic cannulation of the fallopian tubes.
5. Contraindications of Hysteroscopy
5.1 Absolute Contraindications
| Contraindication | Reason / Rationale |
|---|---|
| Active pelvic inflammatory disease (PID) | Risk of spreading infection to peritoneal cavity; sepsis risk |
| Active cervical infection / cervicitis | Risk of ascending infection and sepsis |
| Active uterine / cervical malignancy (known) | Risk of tumour dissemination via distension media |
| Recent uterine perforation | Risk of bowel injury through perforation site |
| Haemodynamic instability | Patient not fit for procedure; anaesthetic risk |
| Uncontrolled coagulopathy | Haemorrhage risk without correction |
| Ongoing intrauterine pregnancy | Risk to foetus; contraindicated where pregnancy is desired |
5.2 Relative Contraindications
| Contraindication | Consideration |
|---|---|
| Heavy active uterine bleeding | Poor visualisation; may be managed with hormonal pretreatment |
| Severe cervical stenosis | Risk of false passage; may require priming with misoprostol |
| Large uterine fibroids (>4 cm intramural) | Limited hysteroscopic access; consider combined approach |
| Coagulopathy (correctable) | Correct INR / platelets prior to procedure |
| Uncontrolled cardiac / pulmonary disease | Anaesthetic risk; optimise before surgery |
| Known uterine cancer (for TCRE) | Ablation inappropriate; formal staging surgery required |
| Desire for future pregnancy (for TCRE) | Ablation destroys endometrium; discuss alternatives |
6. Pre-Operative Assessment and Preparation
6.1 Patient Evaluation
Pre-operative evaluation includes a complete history covering menstrual pattern, obstetric history, prior surgeries, and bleeding disorders; general, abdominal, and pelvic bimanual examination; cervical (Pap) smear to exclude cervical pathology; endometrial biopsy where abnormal uterine bleeding is present, to exclude malignancy pre-operatively; transvaginal ultrasound to assess uterine size, fibroid type and size, endometrial thickness, and polyps; saline infusion sonography where precise delineation of intrauterine pathology is required; and pelvic MRI for large or deep fibroids, to assess intramural extent.
6.2 Laboratory Investigations
Routine pre-operative investigations include complete blood count with blood group and Rh typing; coagulation profile (PT, aPTT, INR); renal and liver function tests; serum electrolytes as a baseline for fluid monitoring; a pregnancy test to exclude intrauterine pregnancy; and cervical swabs where pelvic inflammatory disease is suspected.
6.3 Timing of Procedure
The ideal timing for hysteroscopy is the early proliferative phase, days 6–10 of the cycle, when the endometrium is thin and the cavity is well visualised. TCRE may instead be performed in the secretory phase if preceded by GnRH agonist treatment. Endometrial preparation for TCRE or ablation typically uses GnRH agonists, danazol, or progestogens for 6–12 weeks to thin the endometrium prior to surgery.
6.4 Cervical Priming
Cervical priming may be achieved with misoprostol 400 mcg, given vaginally 3–4 hours before the procedure or sublingually 1–2 hours before; with a laminaria tent for overnight cervical ripening; or, less commonly, with cervical hyaluronidase injection.
7. Operative Technique
7.1 Patient Positioning and Anaesthesia
The patient is positioned in the lithotomy position with adequate hip flexion. Anaesthesia may be general, regional (spinal or epidural), or local with sedation for diagnostic procedures. Bladder catheterisation is performed for longer procedures.
7.2 Step-by-Step Procedure
The procedure begins with consent and administration of anaesthesia, followed by bimanual examination under anaesthesia to assess uterine position and size. Antiseptic preparation and draping are performed, and a vulsellum or tenaculum is applied to the anterior lip of the cervix for traction. Graduated cervical dilatation with Hegar’s dilators is carried out as required for the chosen hysteroscope size. The hysteroscope is inserted under direct vision — never blind — and the cavity is distended with the chosen media, maintaining an intrauterine pressure of 80–100 mmHg, the minimum required to achieve adequate visualisation. Systematic inspection follows a fixed sequence: anterior wall, posterior wall, lateral walls, tubal ostia, and finally the cervical canal on withdrawal of the instrument. Operative intervention is performed as required — resection, ablation, or polypectomy — and all resected tissue is retrieved and submitted for histopathological examination. Fluid balance is carefully assessed throughout, with total inflow and outflow recorded continuously.
8. Trans-Cervical Resection of Sub-Endometrial Fibroid (TCR-F)
Hysteroscopic myomectomy for submucous fibroids is one of the most commonly performed and clinically significant operative hysteroscopic procedures, particularly relevant for women presenting with menorrhagia and infertility.
8.1 FIGO Classification of Submucous Fibroids
| Type | Description | Intramural Component | Surgical Strategy |
|---|---|---|---|
| Type 0 | Pedunculated, entirely intracavitary | 0% | Single-stage complete resection |
| Type 1 | Sessile, <50% intramural | <50% | Usually complete in single stage |
| Type 2 | Sessile, ≥50% intramural | ≥50% | May require staged procedure |
| Type 2-5 | Intramural with endometrial contact | Variable | Combined / laparoscopic approach |
8.2 Surgical Technique for TCR-F
A loop resectoscope is used to shave the fibroid in sequential chips, typically with cutting current of 80–100 W and coagulation current of 60–80 W for monopolar systems. Resection proceeds systematically from distal to proximal. An oxytocin infusion may be used to contract the myometrium and extrude the intramural component into the cavity. All resected chips are retrieved for histopathology, and adequate haemostasis is confirmed before withdrawal of the instrument.
8.3 Tips for Deep Fibroids (Type 2)
Type 2 fibroids with substantial intramural extension often require a two-stage procedure, allowing an interval of approximately three months for the residual intramural component to migrate into the cavity. GnRH agonist therapy between stages reduces vascularity and fibroid volume. Intraoperative ultrasound guidance helps assess residual myometrial thickness, with greater than 8 mm considered a safe margin, and excessive deep resection should be avoided given the risk of uterine perforation.
9. Trans-Cervical Resection of Endometrium (TCRE) / Endometrial Ablation
9.1 Indications
TCRE is indicated for menorrhagia unresponsive to medical treatment, where the patient desires uterine preservation but not further fertility, where hysterectomy is contraindicated, and for dysfunctional uterine bleeding once structural pathology has been excluded.
9.2 Prerequisites (Must Be Met Before TCRE)
Malignancy must be excluded by histopathology; there must be no desire for future pregnancy, and this requires explicit pre-operative counselling; uterine cavity length should be 8 cm or less, or up to 12 cm with caution; and submucous fibroids greater than 3 cm should be treated separately before proceeding to ablation.
Operative Video Library
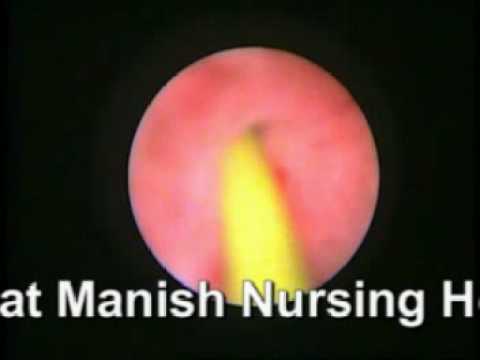
The principles described in this review are illustrated by the following operative video recordings, performed by the author and provided as supplementary educational material for surgeons and gynaecologists learning hysteroscopy. Click any thumbnail to view on YouTube.
9.3 Techniques of Endometrial Ablation
| Technique | Device | Generation | Notes |
|---|---|---|---|
| Transcervical resection (TCRE) | Resectoscope + loop electrode | 1st generation | Gold standard; requires skill |
| Rollerball ablation | Rollerball electrode | 1st generation | Combined with TCRE |
| Thermal balloon ablation | Thermachoice, Cavaterm | 2nd generation | Simpler; less training needed |
| Microwave ablation (MEA) | Microsulis device | 2nd generation | Rapid; predictable depth |
| Bipolar impedance-controlled | NovaSure | 2nd generation | Single use; most popular globally |
| Hydrothermal ablation | Genesys HTA | 2nd generation | Free fluid; good for irregular cavity |
10. Complications of Hysteroscopy
10.1 Intra-Operative Complications
| Complication | Incidence | Management |
|---|---|---|
| Uterine perforation | 0.8–1.5% | Laparoscopy / laparotomy; bowel inspection |
| Fluid overload / media absorption | Up to 5% (TCRE) | Stop procedure; IV furosemide; ICU monitoring |
| Haemorrhage | 1–2% | Balloon tamponade, haemostatic agents, UAE |
| False passage / cervical laceration | 1–3% | Suturing; observe |
| Gas embolism (CO2) | Rare (<0.1%) | Trendelenburg; CPR if needed |
| Electrical injury (monopolar) | Rare | Laparoscopy; bowel repair |
10.2 Post-Operative Complications
Post-operative complications include endometritis or pelvic infection, managed with antibiotics and drainage of any abscess; haematometra, treated by drainage; intrauterine adhesions, which post-operative oestrogen helps to prevent; failure or recurrence of symptoms, requiring re-evaluation and either repeat procedure or hysterectomy; and, in rare cases of pregnancy occurring after TCRE, a high-risk pregnancy that patients should be strongly counselled against pursuing. Cyclic pain following ablation is uncommon but may indicate haematometra.
10.3 Fluid Distension Complications — TURP-Like Syndrome
Excessive absorption of hypotonic distension media such as glycine or sorbitol causes dilutional hyponatraemia, presenting with nausea, headache, visual disturbance, confusion, seizures, pulmonary oedema, and, in severe cases, coma. Risk factors include operative duration exceeding 60 minutes, deep myometrial resection, and high intrauterine pressure. Prevention rests on strict fluid balance monitoring, limiting deficit to under 1000 ml for monopolar systems, and using normal saline with bipolar systems. Management requires immediate cessation of the procedure, intravenous furosemide 40 mg, slow saline correction, and intensive care admission.
11. Quick Reference: Hysteroscopic Procedures at a Glance
| Procedure | Indication | Instrument Used | Key Consideration |
|---|---|---|---|
| Diagnostic hysteroscopy | AUB evaluation, infertility | Diagnostic hysteroscope | No operative intervention |
| Endometrial polypectomy | Polyps on TVS / HSG | Resectoscope / scissors | Submit all tissue for HPE |
| TCR-F (fibroid resection) | Submucous fibroids, AUB, infertility | Resectoscope + loop electrode | FIGO typing guides staging |
| TCRE (endometrial resection) | Menorrhagia, DUB | Resectoscope + loop electrode | Exclude malignancy; no future pregnancy |
| Adhesiolysis (Asherman’s) | IUA, infertility, amenorrhoea | Scissors, laser, electrode | Follow-up with SIS/HSG |
| IUD / RPOC removal | Embedded IUD, retained POC | Grasping forceps / resectoscope | Confirm location on USS first |
| Tubal cannulation | Proximal tubal obstruction | Catheter + guidewire | Success rate ~85% |
12. Learning Objectives for Academic Training
12.1 For Undergraduate Medical Students (MBBS)
Undergraduate learning objectives include defining hysteroscopy and describing the procedure; listing at least eight indications and five contraindications; understanding the basic anatomy relevant to the procedure; recognising common complications and their clinical features; and understanding when to refer a patient to a specialist.
12.2 For Postgraduate Residents (MS/MD)
Postgraduate objectives include performing diagnostic hysteroscopy under supervision; classifying intrauterine pathology such as polyps, fibroids, adhesions, and septa; interpreting hysteroscopic findings and correlating them with imaging; understanding the operative principles of TCRE, TCR-F, and polypectomy; managing intra- and post-operative complications; and counselling patients appropriately before and after the procedure.
12.3 For Senior Surgeons and Gynaecologists
Objectives at this level include performing all hysteroscopic procedures independently; managing Type 2 submucous fibroids using a staged approach; handling intraoperative emergencies including perforation, haemorrhage, and fluid overload; teaching and supervising residents in hysteroscopic skills; and remaining current on new ablation technologies and energy systems.
13. Post-Operative Care and Follow-Up
Immediate post-operative monitoring includes vital signs, fluid balance, and urine output for two to four hours. Analgesia is provided with NSAIDs, with opioids reserved for significant pain. Most procedures are managed on a day-care basis, with admission reserved for complications. Prophylactic antibiotics such as doxycycline or co-amoxiclav are given where indicated. Post-operative hormonal therapy, typically conjugated oestrogens for four to six weeks, is used following adhesiolysis, alongside an intrauterine balloon maintained for one to two weeks. Follow-up review is scheduled at six to eight weeks, with repeat saline infusion sonography or hysterosalpingography where adhesions were treated, and histopathology results are discussed at the follow-up visit.
14. Conclusion
Hysteroscopy has established itself as the gold standard for diagnosis and treatment of intrauterine pathology, offering direct visualisation and, where indicated, definitive surgical management within the same procedure. A sound understanding of relevant anatomy, careful patient selection against absolute and relative contraindications, meticulous attention to fluid balance during operative procedures, and a structured, stepwise operative technique together underpin safe practice. TCRE and TCR-F remain the two most clinically significant operative applications, and staging of submucous fibroids by the FIGO classification provides a practical framework for surgical decision-making. This review, supported by an accompanying operative video supplement, is intended as a practical teaching resource for surgeons and gynaecologists at every stage of training who wish to learn or refine their hysteroscopic practice.
Declarations
- Nature of Article
- This is a review of literature and educational article. It does not present original patient-level case data; the embedded operative videos illustrate the techniques described and were recorded by the author in routine clinical practice.
- Conflict of Interest
- The author declares no conflict of interest.
- Funding
- No funding was received for this work.
- Author Contributions
- Dr. Om Prakash Bhandari: concept, literature review, manuscript preparation, and provision of operative video material (sole author).
References
- American Association of Gynecologic Laparoscopists (AAGL). AAGL Practice Report: Practice Guidelines for the Diagnosis and Management of Submucous Leiomyomas. J Minim Invasive Gynecol. 2012;19(2):152–171.
- Royal College of Obstetricians and Gynaecologists (RCOG). Best Practice in Outpatient Hysteroscopy. Green-top Guideline No. 59. London: RCOG; 2011.
- American College of Obstetricians and Gynecologists (ACOG). Endometrial Ablation. ACOG Practice Bulletin. Obstet Gynecol. 2007;109(5):1233–1248.
- Munro MG, Critchley HOD, Broder MS, Fraser IS. FIGO classification system (PALM-COEIN) for causes of abnormal uterine bleeding in nongravid women of reproductive age. Int J Gynaecol Obstet. 2011;113(1):3–13.
- Wamsteker K, Emanuel MH, de Kruif JH. Transcervical hysteroscopic resection of submucous fibroids for abnormal uterine bleeding: results regarding the degree of intramural extension. Obstet Gynecol. 1993;82(5):736–740.
- Munro MG. Endometrial ablation. Best Pract Res Clin Obstet Gynaecol. 2018;46:120–139.
- Bettocchi S, Ceci O, Vicino M, Marello F, Impedovo L, Selvaggi L. Diagnostic inadequacy of dilatation and curettage. Fertil Steril. 2001;75(4):803–805.
- Jansen FW, Vredevoogd CB, van Ulzen K, Hermans J, Trimbos JB, Trimbos-Kemper TC. Complications of hysteroscopy: a prospective, multicenter study. Obstet Gynecol. 2000;96(2):266–270.